


It’s a culprit in diseases ranging from arthritis to depression
Immunoporosis: Role of Innate Immune Cells in Osteoporosis
Osteoporosis or porous bone disorder is the result of an imbalance in an otherwise highly balanced physiological process known as ‘bone remodeling’. The immune system is intricately involved in bone physiology as well as pathologies. Inflammatory diseases are often correlated with osteoporosis. Inflammatory mediators such as reactive oxygen species (ROS), and pro-inflammatory cytokines and chemokines directly or indirectly act on the bone cells and play a role in the pathogenesis of osteoporosis. Recently, Srivastava et al. (Srivastava RK, Dar HY, Mishra PK. Immunoporosis: Immunology of Osteoporosis-Role of T Cells. Frontiers in immunology. 2018;9:657) have coined the term “immunoporosis” to emphasize the role of immune cells in the pathology of osteoporosis. Accumulated pieces of evidence suggest both innate and adaptive immune cells contribute to osteoporosis. However, innate cells are the major effectors of inflammation. They sense various triggers to inflammation such as pathogen-associated molecular patterns (PAMPS), damage-associated molecular patterns (DAMPS), cellular stress, etc., thus producing pro-inflammatory mediators that play a critical role in the pathogenesis of osteoporosis. In this review, we have discussed the role of the innate immune cells in great detail and divided these cells into different sections in a systemic manner. In the beginning, we talked about cells of the myeloid lineage, including macrophages, monocytes, and dendritic cells. This group of cells explicitly influences the skeletal system by the action of production of pro-inflammatory cytokines and can transdifferentiate into osteoclast. Other cells of the myeloid lineage, such as neutrophils, eosinophils, and mast cells, largely impact osteoporosis via the production of pro-inflammatory cytokines. Further, we talked about the cells of the lymphoid lineage, including natural killer cells and innate lymphoid cells, which share innate-like properties and play a role in osteoporosis. In addition to various innate immune cells, we also discussed the impact of classical pro-inflammatory cytokines on osteoporosis. We also highlighted the studies regarding the impact of physiological and metabolic changes in the body, which results in chronic inflammatory conditions such as ageing, ultimately triggering osteoporosis.

Positive and Negative Affect and Salivary Markers of Inflammation Among Young Adults
Emerging evidence suggests that higher circulating levels of inflammatory biomarkers in blood are associated with higher negative affect (NA) and lower positive affect (PA). To our knowledge, the unique associations between NA and PA in daily life and salivary biomarkers of inflammation have not been examined. This study examined these associations in young adults.

Chronic Infection Depletes Hematopoietic Stem Cells through Stress-Induced Terminal Differentiation
Matatall et al. show that chronic infection causes pancytopenia and hematopoietic stem cell (HSC) depletion in mice. HSCs are lost through impaired self-renewal and increased terminal differentiation, which can be triggered by induction of the interferon gamma-responsive transcription factor BATF2. This study elucidates mechanisms underlying bone marrow failure during chronic infections.

The contribution of gut bacterial metabolites in the human immune signaling pathway of non-communicable diseases
The interaction disorder between gut microbiota and its host has been documented in different non-communicable diseases (NCDs) such as metabolic syndrome, neurodegenerative disease, and autoimmune ...

Osteoporosis in Rheumatoid Arthritis: Dangerous Liaisons
Osteoporosis has been classically considered a comorbidity of rheumatoid arthritis (RA). However, recent advances in the pathogenesis of osteoporosis in RA have shown a close interplay between cells of the immune system and those involved in bone remodeling, introducing new actors into the classic route in which osteoclast activation is related to the RANK/RANKL/OPG pathway. In fact, the inflammatory state in early stages of RA, mediated by interleukin (IL)-1, IL-6, IL-8 and tumour necrosis factor (TNF)-α has the ability to activate and differentiate osteoclasts not only through their relationship with RANKL, but also through the Wnt/DKK1/sclerostin pathway, leading to bone loss. The role of synovial fibroblasts and activated T lymphocytes in the expression of the RANKL system and its connection to bone destruction is also depicted. In addition, autoantibodies such as rheumatoid factor and anti-citrullinated protein antibodies are other pathogenic mechanisms for the development of bone erosions and systemic osteoporosis in RA, even before the onset of arthritis. The aim of this review is to unravel the relationship between different factors involved in the development of osteoporosis in RA patients, both the classic factors and the most novel, based on the relationship of autoantibodies with bone remodeling. Furthermore, we propose that bone mineral density measured by different techniques may be helpful as a biomarker of severity in early arthritis patients.

Osteoimmunology: The Nexus between bone and immune system
Osteoimmunology is an interdisciplinary research field which combines the existing fields of osteology (bone biology) and immunology under one umbrella. The observation that contributed enormously to the emergence of osteoimmunology as an independent field of investigation was the enhanced bone loss in various inflammatory bone diseases such as rheumatoid arthritis, osteoporosis and periodontitis. T helper cells (Th1, Th2, Treg and Th17) along with various other immune cells (B cells, DC, macrophages etc.) are actively involved in bone homeostasis. The present review thus provides an overview of the nexus between these two prominent systems (Bone and Immune system) of an organism, which reside in a common niche (bone marrow) and thus cross-communicate to modulate their respective development. Investigations in the field of osteoimmunology thus promise the advent of new era in the field with novel therapeutics for bone loss in various inflammatory conditions. A molecular insight into the field of osteoimmunology can lead to novel approaches for the prevention and treatment of diverse inflammatory conditions such as osteoporosis, rheumatoid arthritis and osteoarthritis.
Osteoimmunology: The Conceptual Framework Unifying the Immune and Skeletal Systems
The immune and skeletal systems share a variety of molecules, including cytokines, chemokines, hormones, receptors, and transcription factors. Bone cells interact with immune cells under physiological and pathological conditions. Osteoimmunology was created as a new interdisciplinary field in large part to highlight the shared molecules and reciprocal interactions between the two systems in both heath and disease. Receptor activator of NF-κB ligand (RANKL) plays an essential role not only in the development of immune organs and bones, but also in autoimmune diseases affecting bone, thus effectively comprising the molecule that links the two systems. Here we review the function, gene regulation, and signal transduction of osteoimmune molecules, including RANKL, in the context of osteoclastogenesis as well as multiple other regulatory functions. Osteoimmunology has become indispensable for understanding the pathogenesis of a number of diseases such as rheumatoid arthritis (RA). We review the various osteoimmune pathologies, including the bone destruction in RA, in which pathogenic helper T cell subsets [such as IL-17-expressing helper T (Th17) cells] induce bone erosion through aberrant RANKL expression. We also focus on cellular interactions and the identification of the communication factors in the bone marrow, discussing the contribution of bone cells to the maintenance and regulation of hematopoietic stem and progenitors cells. Thus the time has come for a basic reappraisal of the framework for understanding both the immune and bone systems. The concept of a unified osteoimmune system will be absolutely indispensable for basic and translational approaches to diseases related to bone and/or the immune system.

Opinion | Educate Your Immune System (Published 2016)
Our bodies are confused by this 21st-century world.

The gut microbiota in osteoarthritis: where do we stand and what can we do?
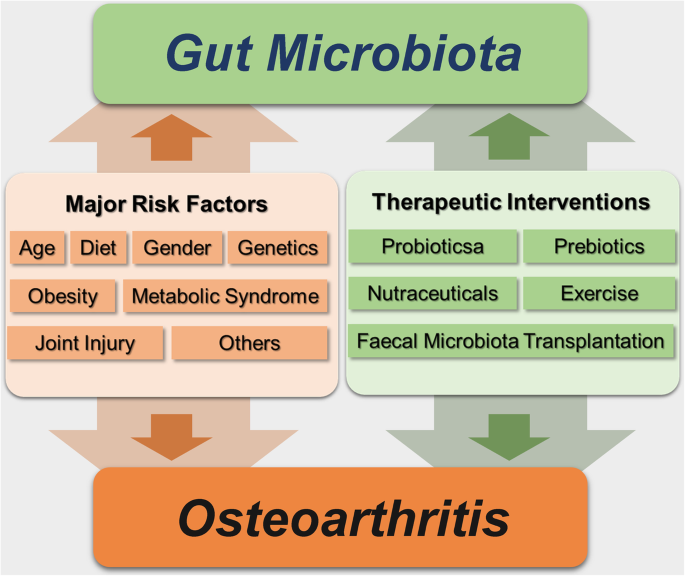
Osteoarthritis (OA) is one of the most frequent musculoskeletal diseases characterized by degeneration of articular cartilage, subchondral bone remodeling, and synovial membrane inflammation, which is a leading cause of global disability, morbidity, and decreased quality of life. Interpreting the potential mechanisms of OA pathogenesis is essential for developing novel prevention and disease-modifying therapeutic interventions. Gut microbiota is responsible for a series of metabolic, immunological, and structural and neurological functions, potentially elucidating the heterogeneity of OA phenotypes and individual features. In this narrative review, we summarized research evidence supporting the hypothesis of a “gut-joint axis” and the interaction between gut microbiota and the OA-relevant factors, including age, gender, genetics, metabolism, central nervous system, and joint injury, elucidating the underlying mechanisms of this intricate interaction. In the context, we also speculated the promising manipulation of gut microbiota in OA management, such as exercise and fecal microbiota transplantation (FMT), highlighting the clinical values of gut microbiota. Additionally, future research directions, such as more convincing studies by the interventions of gut microbiota, the gene regulation of host contributing to or attributed to the specific phenotypes of gut microbiota related to OA, and the relevance of distinct cell subgroups to gut microbiota, are expected. Moreover, gut microbiota is also the potential biomarker related to inflammation and gut dysbiosis that is able to predict OA progression and monitor the efficacy of therapeutic intervention.
Gut, inflammation and osteoporosis: basic and clinical concepts
Chronic inflammatory disorders such as inflammatory bowel diseases (IBD) affect bone metabolism and are frequently associated with the presence of osteoporosis. Bone loss is regulated by various mediators of the immune system such as the pro-inflammatory cytokines tumour necrosis factor-alpha (TNF-α), interleukin-1beta (IL-1β), IL-6, or interferon-gamma. TNF-α, a master cytokine in human IBD, causes bone erosions in experimental models and these effects are exerted by osteoclasts. Other TNF-related cytokines such as receptor activator of nuclear factor kappa B (RANK), its ligand, RANKL, and osteoprotegerin are important mediators in inflammatory processes in the gut and are critically involved in the pathophysiology of bone loss. The awareness and early diagnosis of osteoporosis in states of chronic inflammation, together with applied therapies such as bisphosphonates, may be beneficial in inflammation-associated osteoporosis. Although several mechanisms may contribute to osteoporosis in patients with IBD and coeliac disease, inflammation as an important factor has so far been neglected. As key inflammatory mediators in IBD such as TNF-α are involved in the disease process both in gut and bone, we hypothesise that neutralisation of TNF-α could prove an efficient strategy in the treatment of inflammation-related osteoporosis in the future.
Osteoimmunology: A Current Update of the Interplay Between Bone and the Immune System
Immunology, already a discipline in its own right, has become a major part of many different medical fields. However, its relationship to orthopedics and trauma surgery has unfortunately, and perhaps unjustly, been developing rather slowly. Discover-ies in recent years have emphasized the immense breadth of communication and connection between both systems and, importantly, the highly promising therapeu-tic opportunities.Recent discoveries of factors originally assigned to the immune system have now also been shown to have a significant impact on bone health and disease, which has greatly changed how we approach treatment of bone pathologies. In case of bone fracture, immune cells, especially macrophages, are present through-out the whole healing process, assure defense against pathogens and discharge a complex variety of effectors to regulate bone modelling. In rheumatoid arthritis and osteoporosis, the immune system contributes to the formation of the pathological and chronic conditions. Fascinatingly, prosthesis failure is not at all solely a me-chanical problem of improper strain but works in conjunction with an active contri-bution of the immune system as a reaction to irritant debris from material wear.Unravelling conjoined mechanisms of the immune and osseous systems heralds therapeutic possibilities for ailments of both. Contemplation of the bone as merely an unchanging support pillar is outdated and obsolete. Instead it is manda-tory that this highly diverse network be incorporated in our understanding of the immune system and hematopoiesis.

Immunoporosis: Immunology of Osteoporosis—Role of T Cells
The role of immune system in various bone pathologies such as osteoporosis, osteoarthritis and rheumatoid arthritis is now well established. This had led to the emergence of a modern field of systems biology called as osteoimmunology, an integrated research between fields of immunology and bone biology under one umbrella. Osteoporosis is one of the most common inflammatory bone-loss conditions with more than 200 million individuals affected worldwide. T helper cells along with various other immune cells are major players involved in bone homeostasis. In the present review, we specifically discuss the role of various defined T lymphocyte subsets (Th cells comprising Th1, Th2, Th9, Th17, Th22, regulatory T cells, follicular helper T cells, natural killer T cells, γδ T cells and CD8+ T cells) in the pathophysiology of osteoporosis. The study of the specific role of immune system in osteoporosis has now been proposed by our group as “Immunoporosis: The immunology of osteoporosis” with special emphasis on the role of various subsets of T lymphocytes. The establishment of this new field had been the need of the hour due to the emergence of novel roles of various T cell lymphocytes in accelerated bone loss observed during osteoporosis. Activated T cells either directly or indirectly through the secretion of various cytokines and factors modulate bone health and thereby regulate bone remodelling. Various studies have summarized the role of inflammation in pathogenesis of osteoporosis, but very few reports had delineated the precise role of various T cell subsets in the pathobiology of osteoporosis. The present review thus for the first time clearly highlights and summarizes the role of various T lymphocytes in the development and pathophysiology of osteoporosis, giving birth to a new field of biology termed as “Immunoporosis”. This novel field will thus provide an overview of the nexus between the cellular components of both bone and immune systems, responsible for the observed bone loss in osteoporosis. A molecular insight into the upcoming and novel field of immunoporosis would thus lead to development of innovative approaches for the prevention and treatment of osteoporosis.

<p>The Rising Era of “Immunoporosis”: Role of Immune System in the Pathophysiology of Osteoporosis</p>
We exhaustively revisit the characteristics, mechanism of action, and function of both innate and adaptive immune cells .

Osteopetrosis in mice lacking NF-κB1 and NF-κB2
The nfkbl and nfkb2 genes encode closely related products regulating immune and inflammatory responses1–3. Their role during development and differentiation remains unclear. The generation of nfkb1 null mice (p50−/−) resulted in altered immune responses, but had no effect on development4. Similarly, nfkb2 knockout mice (p52−/−) did not show developmental defects (J.C. et al., manuscript submitted). We have investigated the potential for in vivo compensatory functions of these genes by generating double-knockout mice. The surprising result was that the animals developed osteopetrosis because of a defect in osteoclast differentiation, suggesting redundant functions of NF-κB1 and NF-κB2 proteins in the development of this cell lineage. The osteopetrotic phenotype was rescued by bone marrow transplantation, indicating that the hematopoietic component was impaired. These results define a new mouse osteopetrotic mutant and implicate NF-κB proteins in bone development, raising new directions in the treatment of bone disorders.
IL-17 in synovial fluids from patients with rheumatoid arthritis is a potent stimulator of osteoclastogenesis
1The Institute of Rheumatology, Tokyo Women’s Medical University, Tokyo 162-0054, Japan2Department of Biochemistry, School of Dentistry, Showa University, Tokyo 142-8555, Japan3The Second Department of Pathology, Tokyo Women’s Medical University, Tokyo 162-0054, Japan4St. Vincent’s Institute of Medical Research, Fitzroy, Victoria 3065, Australia
Severity of COVID-19 at elevated exposure to perfluorinated alkylates
Background The course of coronavirus disease 2019 (COVID-19) seems to be aggravated by air pollution, and some industrial chemicals, such as the perfluorinated alkylate substances (PFASs), are immunotoxic and may contribute to an association with disease severity. Methods From Danish biobanks, we obtained plasma samples from 323 subjects aged 30–70 years with known SARS-CoV-2 infection. The PFAS concentrations measured at the background exposures included five PFASs known to be immunotoxic. Register data was obtained to classify disease status, other health information, and demographic variables. We used ordered logistic regression analyses to determine associations between PFAS concentrations and disease outcome. Results Plasma-PFAS concentrations were higher in males, in subjects with Western European background, and tended to increase with age, but were not associated with the presence of chronic disease. Of the study population, 108 (33%) had not been hospitalized, and of those hospitalized, 53 (16%) had been in intensive care or were deceased. Among the five PFASs considered, perfluorobutanoic acid (PFBA) showed an unadjusted odds ratio (OR) of 2.19 (95% confidence interval, CI, 1.39–3.46) for increasing severities of the disease. Among those hospitalized, the fully adjusted OR for getting into intensive care or expiring was 5.18 (1.29, 20.72) when based on plasma samples obtained at the time of diagnosis or up to one week before. Conclusions Measures of individual exposures to immunotoxic PFASs included short-chain PFBA known to accumulate in the lungs. Elevated plasma-PFBA concentrations were associated with an increased risk of a more severe course of COVID-19. Given the low background exposure levels in this study, the role of exposure to PFASs in COVID-19 needs to be ascertained in populations with elevated exposures.