Increasing evidence suggests estrogen and estrogen signaling pathway disturbances across psychiatric disorders. Estrogens are not only crucial in sexual maturation and reproduction but are also highly involved in a wide range of brain functions, such as cognition, memory, neurodevelopment, and neuroplasticity. To add more, the recent findings of its neuroprotective and anti-inflammatory effects have grown interested in investigating its potential therapeutic use to psychiatric disorders. In this review, we analyze the emerging literature on estrogen receptors and psychiatric disorders in cellular, preclinical, and clinical studies. Specifically, we discuss the contribution of estrogen receptor and estrogen signaling to cognition and neuroprotection via mediating multiple neural systems, such as dopaminergic, serotonergic, and glutamatergic systems. Then, we assess their disruptions and their potential implications for pathophysiologies in psychiatric disorders. Further, in this review, current treatment strategies involving estrogen and estrogen signaling are evaluated to suggest a future direction in identifying novel treatment strategies in psychiatric disorders.
Translational Significance of Selective Estrogen Receptor Modulators in Psychiatric Disorders
Accumulating data from various clinical trial studies suggests that adjuvant therapy with ovarian hormones (estrogens) could be effective in reducing cognitive deficit and psychopathological symptoms in women with psychiatric disorders. However, estrogen therapy poses serious limitations and health issues including feminization in men and increased risks of thromboembolism, hot flashes, breast hyperplasia, and endometrium hyperplasia when used for longer duration in older women (aged ≥ 60 years) or in women who have genetic predispositions. On the other hand, selective estrogen receptor modulators (SERMs), which may (or may not) carry some risks of hot flashes, thromboembolism, breast hyperplasia, and endometrial hyperplasia, are generally devoid of feminization effect. In clinical trial studies, adjuvant therapy with tamoxifen, a triphenylethylene class of SERM, has been found to reduce the frequency of manic episodes in patients with bipolar disorder, whereas addition of raloxifene, a benzothiophene class of SERM, to regular doses of antipsychotic drugs has been found to reduce cognitive deficit and psychological symptoms in men and women with schizophrenia, including women with treatment refractory psychosis. These outcomes together with potent neurocognitive, neuroprotective, and cardiometabolic properties suggest that SERMs could be the potential targets for designing effective and safer therapies for psychiatric disorders.
Progesterone – Friend or foe?
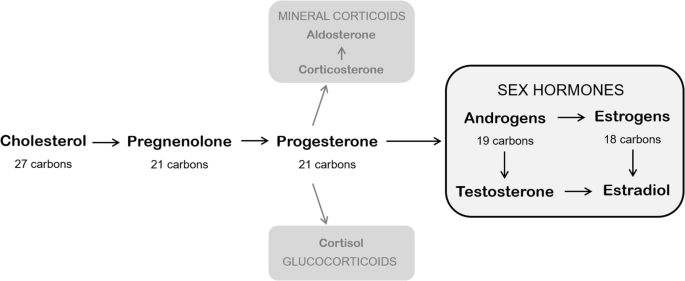
Estradiol is the “prototypic” sex hormone of women. Yet, women have another sex hormone, which is often disregarded: Progesterone. The goal of this article is to provide a comprehensive review on progesterone, and its metabolite allopregnanolone, emphasizing three key areas: biological properties, main functions, and effects on mood in women. Recent years of intensive research on progesterone and allopregnanolone have paved the way for new treatment of postpartum depression. However, treatment for premenstrual syndrome and premenstrual dysphoric disorder as well as contraception that women can use without risking mental health problems are still needed. As far as progesterone is concerned, we might be dealing with a two-edged sword: while its metabolite allopregnanolone has been proven useful for treatment of PPD, it may trigger negative symptoms in women with PMS and PMDD. Overall, our current knowledge on the beneficial and harmful effects of progesterone is limited and further research is imperative.
The steroid metabolome in women with premenstrual dysphoric disorder during GnRH agonist-induced ovarian suppression: effects of estradiol and progesterone addback
Clinical evidence suggests that symptoms in premenstrual dysphoric disorder (PMDD) reflect abnormal responsivity to ovarian steroids. This differential steroid sensitivity could be underpinned by abnormal processing of the steroid signal. We used a pharmacometabolomics approach in women with prospectively confirmed PMDD (n=15) and controls without menstrual cycle-related affective symptoms (n=15). All were medication-free with normal menstrual cycle lengths. Notably, women with PMDD were required to show hormone sensitivity in an ovarian suppression protocol. Ovarian suppression was induced for 6 months with gonadotropin-releasing hormone (GnRH)-agonist (Lupron); after 3 months all were randomized to 4 weeks of estradiol (E2) or progesterone (P4). After a 2-week washout, a crossover was performed. Liquid chromatography/tandem mass spectrometry measured 49 steroid metabolites in serum. Values were excluded if >40% were below the limit of detectability (n=21). Analyses were performed with Wilcoxon rank-sum tests using false-discovery rate (q

Sex Hormones as Cognitive Enhancers?
Understanding the differences in the way women and men think has made headway thanks to experiments showing how sex hormones influence cognitive capacities. Masculine and feminine sex hormones (androgens and estrogens, respectively) affect cognition in different ways and may account for some of the gender differences in cognitive abilities, allowing men and women to perform better in certain cognitive tests. In this opinion article, we discuss studies addressing differences in cognitive functions between males and females and the underlying neural substrates, as well as the effects of sex hormone supplementation. Even though some studies on patients receiving exogenous sex hormones showed gender differences that emerge at group levels on a few cognitive tasks, it is not yet clear whether these differences can be partially attributed to hormonal causes. Supplementation of female estrogen can enhance verbal skills, whereas masculine androgen can increase performance in mathematical and visuospatial tasks. Studies of the administration of exogenous sex hormones have allowed further insight into the use of sex hormones as possible cognitive enhancers.
A Review of Selective Estrogen Receptor Modulators and their Potential for Transfeminine Hormone Therapy
A Review of Selective Estrogen Receptor Modulators and their Potential for Transfeminine Hormone Therapy by Lain
5α-Reductase Inhibition Prevents the Luteal Phase Increase in Plasma Allopregnanolone Levels and Mitigates Symptoms in Women with Premenstrual Dysphoric Disorder
Changes in neurosteroid levels during the luteal phase of the menstrual cycle may precipitate affective symptoms. To test this hypothesis, we stabilized neurosteroid levels by administering the 5α-reductase inhibitor dutasteride to block conversion of progesterone to its neurosteroid metabolite allopregnanolone in women with premenstrual dysphoric disorder (PMDD) and in asymptomatic control women. Sixteen women with prospectively confirmed PMDD and 16 control women participated in one of two separate randomized, double-blind, placebo-controlled, cross-over trials, each lasting three menstrual cycles. After one menstrual cycle of single-blind placebo, participants were randomized to receive, for the next two menstrual cycles, either double-blind placebo or dutasteride (low-dose 0.5 mg/day in the first eight PMDD and eight control women or high-dose 2.5 mg/day in the second group of women). All women completed the daily rating form (DRF) and were evaluated in clinic during the follicular and luteal phases of each menstrual cycle. Main outcome measures were the DRF symptoms of irritability, sadness, and anxiety. Analyses were performed with SAS PROC MIXED. In the low-dose group, no significant effect of dutasteride on PMDD symptoms was observed compared with placebo (ie, symptom cyclicity maintained), and plasma allopregnanolone levels increased in women with PMDD from follicular to the luteal phases, suggesting the absence of effect of the low-dose dutasteride on 5α-reductase. In contrast, the high-dose group experienced a statistically significant reduction in several core PMDD symptoms (ie, irritability, sadness, anxiety, food cravings, and bloating) on dutasteride compared with placebo. Dutasteride had no effect on mood in controls. Stabilization of allopregnanolone levels from the follicular to the luteal phase of the menstrual cycle by blocking the conversion of progesterone to its 5α-reduced neurosteroid metabolite mitigates symptoms in PMDD. These data provide preliminary support for the pathophysiologic relevance of neurosteroids in this condition.
Progesterone and plasma metabolites in women with and in those without premenstrual dysphoric disorder
BACKGROUND: The molecular mechanisms underpinning the progesterone-triggering mood symptoms in women with premenstrual dysphoric disorder (PMDD) are unknown. Cell metabolism is a potential source of variability. Very little is known about the effect of progesterone sensitivity on the metabolome. In this study, we aimed to characterize the effects of progesterone on the global metabolic profile and explore the differences between women with PMDD and controls. METHODS: Plasma was obtained from 12 women with prospectively confirmed PMDD and 25 controls under two hormone conditions: (1) gonadal suppression induced by leuprolide acetate (3.75 mg IM monthly) and (2) add-back phase with leuprolide and progesterone (200 mg twice daily by vaginal suppository). The global metabolic profile was obtained using liquid and gas chromatography followed by mass spectrometry. Differences between groups and time points were tested using repeated measures analysis of variance. The false discovery rate was calculated to account for multiple testing. RESULTS: Amino acids and their derivatives represented 78% (28/36) of the known compounds that were found in significantly lower plasma concentrations after progesterone administration than during gonadal suppression. The concentration of tyrosine was nominally significantly decreased after progesterone add-back in controls, but not in cases (P = 0.02). CONCLUSION: Plasma levels of some amino acids are decreased in response to progesterone. Albeit preliminary, evidence further suggests that progesterone has a different effect on the metabolic profiles of women with PMDD compared to controls. Further research is needed to replicate our findings in a larger sample and to identify the unknown compounds, especially those differentially expressed.
Critical Role of Estrogens on Bone Homeostasis in Both Male and Female: From Physiology to Medical Implications
Bone is a multi-skilled tissue, protecting major organs, regulating calcium phosphate balance and producing hormones. Its development during childhood determines height and stature as well as resistance against fracture in advanced age. Estrogens are key regulators of bone turnover in both females and males. These hormones play a major role in longitudinal and width growth throughout puberty as well as in the regulation of bone turnover. In women, estrogen deficiency is one of the major causes of postmenopausal osteoporosis. In this review, we will summarize the main clinical and experimental studies reporting the effects of estrogens not only in females but also in males, during different life stages. Effects of estrogens on bone involve either Estrogen Receptor (ER)α or ERβ depending on the type of bone (femur, vertebrae, tibia, mandible), the compartment (trabecular or cortical), cell types involved (osteoclasts, osteoblasts and osteocytes) and sex. Finally, we will discuss new ongoing strategies to increase the benefit/risk ratio of the hormonal treatment of menopause.

Estrogens and Androgens in Skeletal Physiology and Pathophysiology
Estrogens and androgens influence the growth and maintenance of the mammalian skeleton and are responsible for its sexual dimorphism. Estrogen deficiency at menopause or loss of both estrogens and androgens in elderly men contribute to the development of osteoporosis, one of the most common and impactful metabolic diseases of old age. In the last 20 years, basic and clinical research advances, genetic insights from humans and rodents, and newer imaging technologies have changed considerably the landscape of our understanding of bone biology as well as the relationship between sex steroids and the physiology and pathophysiology of bone metabolism. Together with the appreciation of the side effects of estrogen-related therapies on breast cancer and cardiovascular diseases, these advances have also drastically altered the treatment of osteoporosis. In this article, we provide a comprehensive review of the molecular and cellular mechanisms of action of estrogens and androgens on bone, their influences on skeletal homeostasis during growth and adulthood, the pathogenetic mechanisms of the adverse effects of their deficiency on the female and male skeleton, as well as the role of natural and synthetic estrogenic or androgenic compounds in the pharmacotherapy of osteoporosis. We highlight latest advances on the crosstalk between hormonal and mechanical signals, the relevance of the antioxidant properties of estrogens and androgens, the difference of their cellular targets in different bone envelopes, the role of estrogen deficiency in male osteoporosis, and the contribution of estrogen or androgen deficiency to the monomorphic effects of aging on skeletal involution.

When Women Initiate Estrogen Therapy Matters | The Menopause Society
New large-scale analysis shows potential long-term benefits of initiating hormones during perimenopause

Premenstrual Dysphoric Disorder Symptoms Following Ovarian Suppression: Triggered by Change in Ovarian Steroid Levels But Not Continuous Stable Levels | American Journal of Psychiatry
Objective:Premenstrual dysphoric disorder (PMDD) symptoms are eliminated by ovarian suppression and stimulated by administration of ovarian steroids, yet they appear with ovarian steroid levels indistinguishable from those in women without PMDD. Thus, ...

Selective estrogen receptor modulators in clinical practice: a safety overview
Introduction: Selective estrogen receptor (ER) modulators (SERMs) are a class of nonsteroidal compounds that interact with ERs, each with a distinct tissue-specific profile. Depending upon the degr...

Estrogen therapy for osteoporosis in the modern era
Menopause predisposes women to osteoporosis due to declining estrogen levels. This results in a decrease in bone mineral density (BMD) and an increase in fractures. Osteoporotic fractures lead to substantial morbidity and mortality, and are considered one of the largest public health priorities by the World Health Organization (WHO). It is therefore essential for menopausal women to receive appropriate guidance for the prevention and management of osteoporosis. The Women’s Health Initiative (WHI) randomized controlled trial first proved hormonal therapy (HT) reduces the incidence of all osteoporosis-related fractures in postmenopausal women. However, the study concluded that the adverse effects outweighed the potential benefits on bone, leading to a significant decrease in HT use for menopausal symptoms. Additionally, HT was not used as first-line therapy for osteoporosis and fractures. Subsequent studies have challenged these initial conclusions and have shown significant efficacy of HT in various doses, durations, regimens, and routes of administration. These studies support that HT improves BMD and reduces fracture risk in women with and without osteoporosis. Furthermore, the studies suggest that low-dose and transdermal HT are less likely associated with the adverse effects of breast cancer, endometrial hyperplasia, coronary artery disease (CAD), and venous thromboembolism (VTE) previously observed in standard-dose oral HT regimens. Given the need for estrogen in menopausal women and evidence supporting the cost effectiveness, safety, and efficacy of HT, we propose that HT should be considered for the primary prevention and treatment of osteoporosis in appropriate candidates. HT should be individualized and the once “lowest dose for shortest period of time” concept should no longer be used. This review will focus on the prior and current studies for various HT formulations used for the prevention and treatment of osteoporosis, exploring the safety profile of low-dose and transdermal HT that have been shown to be safer than oral standard-dose HT.

Estrogen and the skeleton
Estrogen is the major hormonal regulator of bone metabolism in women and men. Therefore, there is considerable interest in unraveling the pathways by which estrogen exerts its protective effects on bone. Although the major consequence of the loss of estrogen is an increase in bone resorption, estrogen deficiency is associated with a gap between bone resorption and formation, indicating that estrogen is also important for maintaining bone formation at the cellular level. Direct estrogen effects on osteocytes, osteoclasts, and osteoblasts lead to inhibition of bone remodeling, decreased bone resorption, and maintenance of bone formation, respectively.

Microdosing Estrogen
Learn about microdosing estrogen regimens and their effects from a quick guide to feminizing hormone therapy.

The Role of Estrogen in the Control of Rat Osteocyte Apoptosis
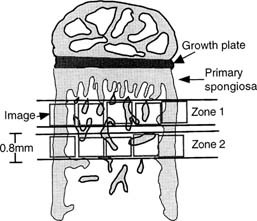
Abstract We have previously shown that estrogen withdrawal by gonadotrophin-releasing hormone analogs (GnRHa) induces osteocyte death via apoptosis in human bone. Although it is likely that the increase in osteocyte death via apoptosis was related to the loss of estrogen, these experiments could not rule out a direct role for the GnRHa. Therefore, in this study, we have used a rat model of ovariectomy (OVX) to determine whether the effect of estrogen withdrawal extends to other species and to clarify the role of estrogen in the maintenance of osteocyte viability. Twelve 9-week-old rats were divided into three treatment groups: sham operated (SHAM) (n = 4), OVX (n = 4), and OVX + estrogen (E2) (25 μg/day) (n = 4). At 3 weeks following the start of treatment, tibial bones were removed. The percentage of osteocytes displaying DNA breaks, using an in situ nick-translation method, was significantly higher in the OVX group compared with the SHAM control in both cortical bone (10.04% vs. 2.31%, respectively; p < 0.0001) and trabecular bone (6.44% vs. 1.58%, respectively; p = 0.003). Addition of estrogen in the OVX animals completely abrogated the increase in osteocyte apoptosis in cortical bone (0.78%) and trabecular bone (1.17%). The percentage of apoptotic osteocytes decreased with increasing distance from the primary/secondary spongiosa interface below the growth plate in the OVX model and the OVX + E2 model. Nuclear morphology and electrophoresis of DNA confirmed the presence of apoptotic cells in the samples. In conclusion, OVX in the rat results in an increase in osteocyte apoptosis as a direct or indirect result of E2 loss. Addition of estrogen in the OVX animals prevents this increase in osteocyte apoptosis. These data confirm an important role for estrogen in the control of osteocyte apoptosis and the maintenance of osteocyte viability. Estrogen deficiency might, through compromising the viability of osteocyte networks, reduce the ability of bone to respond appropriately to loading.